News › Beijing
From Hours-Long IV Infusion to a ~5-Minute Subcutaneous Injection: What the New Amivantamab Formulation Changes
Published 16 Oct 2026 · 7-min read · Beijing Network News

For patients who need long-term anti-tumor therapy, the treatment experience depends not only on how well a medicine works, but also on infusion time, the infusion process, infusion-related reactions and the travel time to and from the hospital.
On 22 December 2025, the Chinese prescribing information for amivantamab injection (subcutaneous) — brand name RYBREVANT FASPRO — was officially approved. The new formulation keeps amivantamab’s dual EGFR and MET targeting, and by adding recombinant human hyaluronidase it switches the original intravenous infusion to an abdominal subcutaneous injection that takes about 5 minutes per dose.
Amivantamab subcutaneous formulation is already approved and in clinical use in mainland China. In Hong Kong the formulation has not yet completed its routine registration, but eligible patients may, after physician assessment, access it through the Named Patient Program (NPP) and the unregistered-drug individual import procedure.
Going from a multi-hour intravenous infusion to a roughly 5-minute subcutaneous injection is not only a change in the route of administration: it is also expected to shorten the time spent in the treatment chair, lower infusion-related reactions, and simplify parts of the treatment workflow.
What is the amivantamab subcutaneous formulation?
Amivantamab injection (subcutaneous) is an imported, original-research EGFR/MET bispecific antibody. Its generic name is amivantamab injection (subcutaneous) and its brand name is RYBREVANT FASPRO®. It targets EGFR and MET, is manufactured by Janssen-Cilag International NV and Xi’an Janssen Pharmaceutical Co., Ltd., and is given as an abdominal subcutaneous injection by trained medical staff — about 5 minutes per dose.
Approved indications
Amivantamab subcutaneous injection is approved in China for the following uses in adult patients:
- In combination with lazertinib, for first-line treatment of locally advanced or metastatic non-small cell lung cancer (NSCLC) whose tumors carry an EGFR exon 19 deletion or exon 21 L858R substitution mutation.
- In combination with carboplatin and pemetrexed, for locally advanced or metastatic non-squamous NSCLC with an EGFR exon 19 deletion or exon 21 L858R substitution mutation that has progressed on or after EGFR tyrosine kinase inhibitor (TKI) therapy.
- In combination with carboplatin and pemetrexed, for first-line treatment of locally advanced or metastatic NSCLC confirmed to carry an EGFR exon 20 insertion mutation.
How does amivantamab work?
In some types of NSCLC, EGFR mutations keep driving tumor-cell proliferation and survival signals, while the MET pathway can contribute to tumor growth and treatment resistance. Amivantamab is a bispecific antibody that targets the extracellular domains of both EGFR and MET, and it works through several pathways:
- It binds EGFR and MET on the tumor-cell surface at the same time, blocking ligands from attaching to their receptors.
- It promotes degradation of EGFR and MET receptors, reducing abnormal signaling on the cell surface.
- It inhibits downstream pathways involved in tumor-cell proliferation, survival and resistance.
- It engages immune effector cells such as natural killer cells and macrophages to help clear EGFR- or MET-expressing tumor cells through antibody-dependent cellular cytotoxicity and trogocytosis.
Image source: RYBREVANT FASPRO® official introduction.
Subcutaneous versus intravenous: what changes?
The PALOMA-3 study compared the subcutaneous and intravenous formulations of amivantamab, both combined with lazertinib. Here is what changed for patients:
| Aspect | Subcutaneous | Intravenous |
|---|---|---|
| Median injection or infusion time at first dose | 4.8 minutes | 5.0 hours |
| Median time at later doses | 4.8 minutes | 2.3 hours |
| Administration-related reactions | 13% | 66% |
| Grade 3 reactions | 0.5% | 3.8% |
Note: “about 5 minutes” refers to the amivantamab injection itself. Patients still need pre-treatment assessment, premedication and post-dose observation, and any chemotherapy given with it is still infused intravenously.
01 — Shorter administration time
In the PALOMA-3 study, the median subcutaneous injection time at first dose was 4.8 minutes, while the median intravenous infusion time at first dose was 5.0 hours. At later visits the subcutaneous injection remained about 4.8 minutes and the intravenous infusion about 2.3 hours.
02 — A simpler first-dose process
The traditional intravenous first dose of amivantamab is usually split over two days to lower the risk of infusion-related reactions. The subcutaneous formulation is given as an abdominal injection on the same day per the relevant protocol — no intravenous line is needed for amivantamab, and the first dose does not have to be split across two days.
03 — Far fewer administration-related reactions
In PALOMA-3, both groups also received lazertinib. The administration-related reaction rate was 13% with the subcutaneous formulation versus 66% with the intravenous formulation, and grade 3 reactions were 0.5% versus 3.8%. In other words, the subcutaneous formulation cuts administration-related reactions by roughly four-fifths. The risk does not disappear entirely, however: 89% of subcutaneous administration-related reactions occurred after the first dose, so the first treatment still needs full premedication and must take place in a setting with monitoring, supportive care and resuscitation capability.
04 — Comparable exposure and response
PALOMA-3 was a randomized, open-label phase III study that enrolled 418 patients with EGFR-mutant advanced NSCLC who had progressed on or after osimertinib and platinum-based chemotherapy. They received either subcutaneous amivantamab plus lazertinib or intravenous amivantamab plus lazertinib. The subcutaneous formulation was non-inferior to the intravenous one on key pharmacokinetic measures; objective response rate was 30.1% versus 32.5% (meeting the pre-specified non-inferiority margin); median progression-free survival was 6.11 versus 4.30 months; and median duration of response was 11.17 versus 7.06 months. Progression-free and response durations were numerically longer in the subcutaneous arm, but PALOMA-3 was designed mainly to confirm pharmacokinetic and response non-inferiority, so it should not be read as proof that the subcutaneous formulation is superior in anti-tumor efficacy.
Can the subcutaneous formulation replace the intravenous one directly?
It must not be switched on your own. Although both contain the same anti-tumor antibody, their concentration, recommended dose and administration schedule differ:
- The subcutaneous dose is set by baseline body weight and the combination regimen.
- With lazertinib, dosing is usually weekly at first, then every two weeks.
- With carboplatin and pemetrexed, it is usually given every three weeks thereafter.
The exact dose, frequency and switch between formulations must be decided by an oncology physician with relevant experience, following the latest prescribing information.
What about safety?
The subcutaneous route mainly improves administration time and administration-related reactions, but amivantamab itself and the toxicities of combination therapy still need attention. In PALOMA-3, the more common adverse events with subcutaneous amivantamab plus lazertinib included rash (80%), nail toxicity (58%), musculoskeletal pain (50%), fatigue (37%), oral mucositis (36%), edema (34%), nausea (30%) and local injection-site reaction (11%, with no grade 3 or 4 local reactions reported). During treatment, the following also need attention:
- Administration-related reactions — may appear as breathlessness, flushing, fever, chills, chest discomfort, low blood pressure or vomiting. Even with the subcutaneous formulation, premedication with an antihistamine, antipyretic and, when needed, corticosteroids remains necessary per the label.
- Skin and nail toxicity — strengthen moisturizing, sun protection and skin care before and during treatment, with preventive or therapeutic medication when appropriate.
- Interstitial lung disease or pneumonitis — seek prompt medical assessment for new or worsening breathlessness, cough or fever.
- Venous thromboembolism — especially when combined with lazertinib; the label recommends prophylactic anticoagulation during the first four months, while weighing thrombosis and bleeding risk.
- Ocular toxicity — report eye pain, dry eye, red conjunctiva, blurred vision or other visual changes to the care team without delay.
- Combination-chemotherapy toxicity — when given with carboplatin and pemetrexed, monitor blood counts, liver and kidney function and electrolytes.
So the subcutaneous formulation does not mean self-injection at home, nor does it remove the need for premedication and post-dose observation. Its value is to shorten amivantamab administration time markedly while keeping drug exposure and objective response comparable.
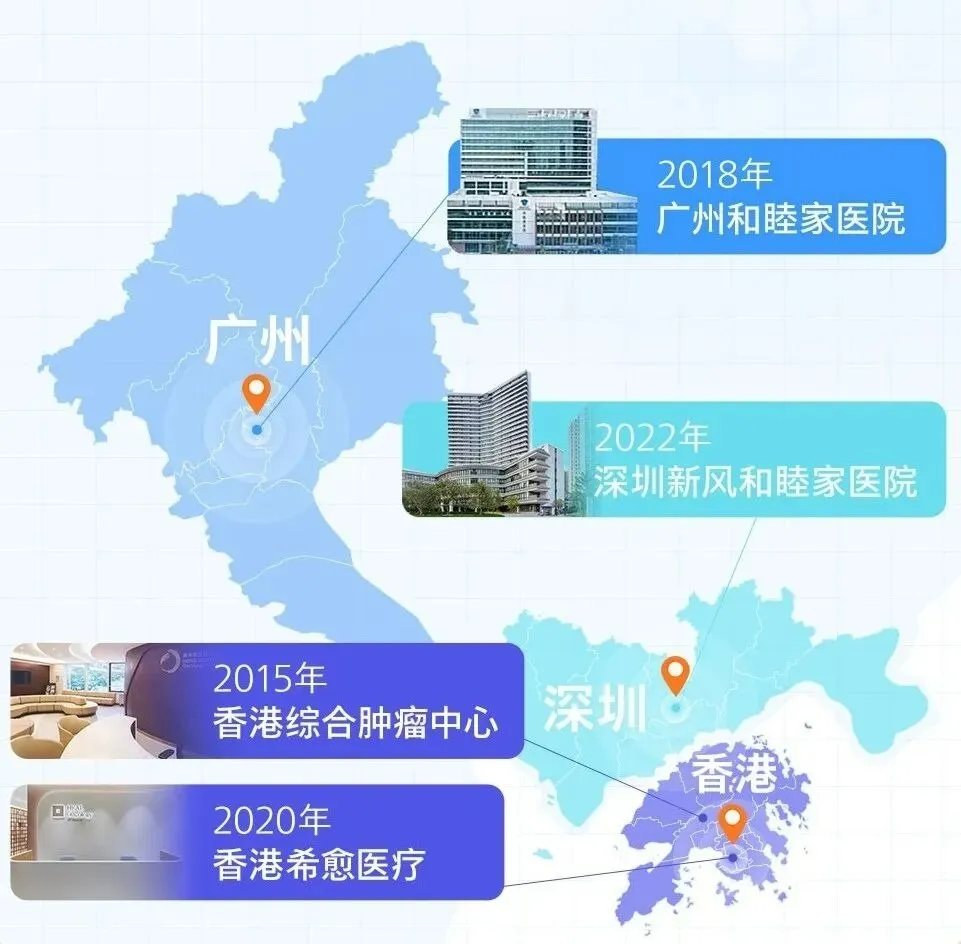
United Family Healthcare’s integrated oncology network across the Greater Bay Area and beyond.
Tracking the international frontier, offering individualized choices
United Family Healthcare builds its oncology program with an international outlook, putting patients’ survival benefit, quality of life and treatment experience first. It follows the latest advances from international oncology congresses such as ASCO, ESMO and WCLC, and brings in diverse anti-tumor options including targeted therapy, immunotherapy, antibody-drug conjugates and domestic innovative drugs.
In clinical practice, oncology, pharmacy and nursing teams work together on assessment, planning, medication management, adverse-event monitoring and follow-up support, so that patients receive care that is as precise, safe and individualized as possible on a standardized foundation.
For adult patients with EGFR-mutant locally advanced or metastatic NSCLC, whether the subcutaneous amivantamab formulation is appropriate requires a comprehensive assessment of the EGFR mutation subtype, treatment line, prior EGFR TKI and platinum-based chemotherapy, the combination regimen, baseline body weight, pulmonary status, skin and ocular condition, and thrombosis and bleeding risk.
The subcutaneous formulation can substantially shorten amivantamab administration time, but standardized pre-medication, first-dose monitoring, skin and nail management, thrombosis-risk assessment and respiratory follow-up remain essential. The care team must also set anticoagulation, skin-prevention and laboratory-monitoring plans according to the combination, so that a simpler administration route truly becomes a more continuous and composed treatment experience.
The value of an innovative drug lies not only in refreshing clinical data, but in genuinely becoming an accessible treatment choice for patients through standardized, humane medical care.
This article is for disease and medication education only and does not constitute individualized medical advice for any patient. For indications, dosage, adverse reactions and precautions, please refer to the latest approved prescribing information from the national drug regulatory authority.
References:
- Amivantamab injection (subcutaneous) prescribing information, approval date 22 December 2025, Xi’an Janssen Pharmaceutical Co., Ltd.
- Leighl NB, et al. Subcutaneous Versus Intravenous Amivantamab, Both in Combination With Lazertinib, in Refractory EGFR-Mutated NSCLC: Primary Results From the Phase III PALOMA-3 Study. J Clin Oncol. 2024;42(30):3593-3605.
- Alexander M, et al. Patient Satisfaction and Resource Utilization Results From the PALOMA-3 Study. Eur J Cancer. 2025;227:115624.
- DXY Medication Assistant: amivantamab injection (subcutaneous) drug information.
Source: Beijing United Family Hospital WeChat article, 16 Oct 2026.